
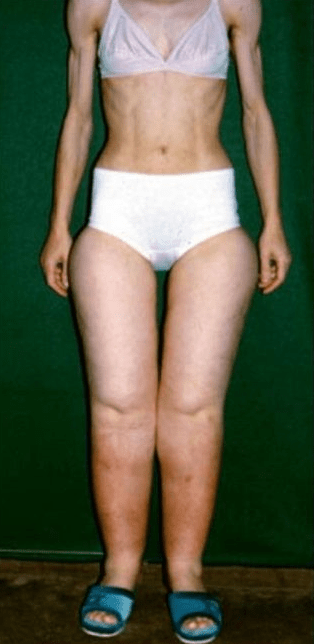
Could iodine deficiency play a role in the development of lipedema? One physician believed the connection was far more significant than most people realize.
Lipedema is a chronic condition characterized by disproportionate fat accumulation, most commonly affecting the legs, hips, and arms. Women with lipedema frequently experience tenderness, pain, easy bruising, and fat deposits that resist conventional weight-loss efforts.
Although lipedema is increasingly recognized as a distinct medical condition, its underlying causes remain incompletely understood.
Hormonal influences, genetic predisposition, connective tissue abnormalities, and inflammation have all been investigated. But one possible connection has received relatively little attention: iodine deficiency.
Dr. Jorge Flechas, a physician involved in the Iodine Project alongside Drs. Guy Abraham and David Brownstein, proposed that inadequate iodine availability within adipose tissue could contribute to the characteristic fat enlargement seen in lipedema.
His hypothesis raises an intriguing question: Could iodine have a role in lipedema beyond its well-known function in thyroid hormone production?
Dr. Jorge Flechas: Lipedema as a Goiter of the Fat Cells
In an interview discussing iodine and women’s reproductive health, Dr. Flechas presented a provocative explanation for lipedema.
He suggested that iodine deficiency might produce enlargement in tissues beyond the thyroid gland.
When the thyroid enlarges in response to certain forms of iodine deficiency, the resulting condition is known as a goiter. Flechas proposed that a comparable process could occur in adipose tissue, producing the disproportionate enlargement characteristic of lipedema.
He described this as a “goiter of the fat cells.”
Flechas also discussed observations of women in iodine-deficient regions of South America who exhibited both thyroid enlargement and disproportionate lower-body fat accumulation.
Additionally, he drew comparisons between the tissue abnormalities observed in lipedema and those associated with fibrocystic breast disease, another condition he believed could respond to iodine supplementation.
These observations formed part of his argument that iodine requirements extend beyond the thyroid gland.
However, Flechas’s interpretation remains a hypothesis rather than an established explanation for lipedema. Similar appearances or clinical observations do not establish that iodine deficiency causes abnormal adipose tissue growth. Controlled research demonstrating that iodine supplementation reverses lipedema is currently lacking.
Read Dr. Flechas’s interview on iodine and women’s health
Iodine Does More Than Support the Thyroid
Iodine is an essential micronutrient best known for its role in producing thyroid hormones, which influence metabolism, growth, and numerous physiological processes.
However, the thyroid is not the only tissue capable of taking up iodine.
The breasts, salivary glands, and certain other tissues have iodine-related transport systems and biological functions.
This wider distribution has led researchers to investigate whether iodine may participate in antioxidant activity, cellular signaling, and tissue regulation beyond its thyroid-specific functions.
Advocates of iodine supplementation, including Flechas and Brownstein, have argued that iodine needs throughout the body may be substantially greater than conventional nutritional recommendations suggest.
That possibility is particularly interesting in lipedema, where altered adipose tissue biology and connective tissue changes are important features of the disease.
Nevertheless, the presence of iodine in a tissue does not establish that high-dose supplementation improves its function, nor does it establish that iodine deficiency causes lipedema.
Those questions require direct clinical investigation.
The High-Dose Iodine Protocol
Drs. Abraham, Flechas, and Brownstein became associated with an approach sometimes called orthoiodosupplementation.
Unlike conventional nutritional recommendations, which measure iodine requirements in micrograms, this approach frequently uses doses measured in milligrams.
One commonly described target is 50 mg of iodine and iodide daily, often supplied by preparations such as Iodoral or Lugol’s solution.
For perspective:
- The recommended dietary allowance for a nonpregnant adult is 150 micrograms (0.15 mg) per day.
- The established U.S. adult tolerable upper intake level is 1,100 micrograms (1.1 mg) per day.
- A 50 mg protocol provides approximately 333 times the adult recommended dietary allowance and 45 times the tolerable upper intake level, before accounting for dietary iodine.
Components of the protocol
The following describes a commonly circulated version of the iodine protocol associated with these physicians. It is provided to explain the approach, not as a recommendation to follow it.
| Component | Commonly described amount |
|---|---|
| Iodine/iodide | 12.5–50 mg daily, sometimes gradually increased |
| Selenium | 200 mcg daily |
| Vitamin C | Approximately 3,000 mg daily |
| Magnesium | 300–600 mg daily |
| Vitamin B2 (riboflavin) | 300 mg daily |
| Vitamin B3 (niacin) | 1,000 mg daily |
| Unrefined salt | Often additional salt or salt-water intake |
Protocol advocates describe selenium, magnesium, vitamin C, and B vitamins as supporting iodine utilization and antioxidant defenses.
They also commonly discuss a practice called salt loading, intended to promote the elimination of bromide and other halides.
However, there is insufficient clinical evidence that salt loading prevents iodine toxicity or that these additional supplements make high-dose iodine treatment safe. Excess selenium, niacin, supplemental magnesium, vitamin C, and sodium can themselves produce adverse effects.
Importantly, this protocol has not been validated as a treatment for lipedema in controlled clinical trials.
People considering iodine beyond conventional nutritional doses should consult a clinician familiar with thyroid physiology and iodine-related risks rather than attempting the protocol independently.
Why Does This Conflict With Conventional Medical Recommendations?
This is where the discussion becomes particularly interesting.
The American Thyroid Association advises against routine iodine supplementation exceeding 500 micrograms daily and identifies 1,100 micrograms as the adult tolerable upper intake level.
These recommendations are based partly on evidence that excessive iodine exposure can disrupt thyroid function.
One of the principal concerns involves a physiological response known as the Wolff–Chaikoff effect.
What Is the Wolff–Chaikoff Effect?
First described in 1948, the Wolff–Chaikoff effect refers to a temporary reduction in thyroid hormone synthesis in response to a substantial iodine exposure.
In most healthy individuals, the thyroid adapts to the increased iodine availability and resumes normal hormone production. This adaptation is commonly called escape from the Wolff–Chaikoff effect.
However, certain individuals may not adapt normally, particularly those with underlying thyroid disease.
Excess iodine exposure has been associated with both hypothyroidism and hyperthyroidism, depending on the individual and their underlying thyroid physiology.
This is one reason mainstream endocrinology discourages routine high-dose iodine supplementation.
Why Dr. Brownstein Challenges the Conventional View
Dr. David Brownstein, author of Iodine: Why You Need It, Why You Can’t Live Without It, has long advocated for a broader reconsideration of iodine requirements.
Alongside Dr. Guy Abraham and Dr. Jorge Flechas, Brownstein questioned whether the original Wolff–Chaikoff research was being interpreted too broadly when applied to human iodine supplementation.
In writings associated with their iodine research, the physicians reported that they had not observed the predicted thyroid-suppressing effects among approximately 4,000 patients receiving daily iodine doses ranging from 12.5 to 50 mg, in some cases for several years.
They argued that these clinical experiences were inconsistent with the prevailing concerns surrounding high-dose iodine.
These observations are worth understanding, but there is an important scientific distinction.
Reports from clinical practices do not provide the same degree of evidence as controlled trials, particularly without detailed information about patient selection, thyroid laboratory results, adverse-event monitoring, and long-term outcomes.
Furthermore, the absence of an observed complication in a particular clinical population does not establish that the complication cannot occur.
Modern endocrine research continues to recognize both the Wolff–Chaikoff effect and cases of iodine-induced thyroid dysfunction.
The disagreement, therefore, is not simply whether iodine is essential. Both sides agree that it is. The disagreement concerns how much iodine is appropriate, whether higher doses offer additional benefits, and whether those potential benefits outweigh the documented risks.
Could Iodine Help Women With Lipedema?
The answer remains unknown.
Flechas’s hypothesis is interesting because it attempts to connect several observations: the hormonal associations of lipedema, abnormal adipose tissue enlargement, iodine’s functions outside the thyroid, and the historical use of iodine for certain breast conditions.
But a biologically plausible hypothesis is not the same as a demonstrated treatment.
To establish whether iodine supplementation benefits women with lipedema, researchers would need controlled studies measuring outcomes such as:
- Lipedema pain and tenderness
- Limb circumference and tissue volume
- Adipose tissue structure and fibrosis
- Functional limitations and quality of life
- Thyroid function and treatment-related adverse effects
Studies would also need to determine whether any apparent benefit relates to correcting genuine iodine deficiency or to iodine exposure substantially beyond normal nutritional requirements.
Until such research is available, claims that high-dose iodine can reverse or cure lipedema should be viewed cautiously.
Final Thoughts: A Question Worth Investigating
Women with lipedema understand the frustration of living with a condition that remains poorly understood.
For years, many have been told that their disproportionate fat accumulation is simply the consequence of overeating or insufficient exercise, despite the distinctive biological characteristics of lipedema tissue.
It is understandable that patients continue exploring overlooked mechanisms and potential interventions.
Dr. Jorge Flechas’s proposed connection between iodine deficiency and lipedema deserves examination as a scientific hypothesis. His ideas challenge us to consider whether iodine’s functions outside the thyroid could be relevant to abnormal adipose tissue biology.
At the same time, challenging conventional recommendations requires strong evidence, especially when the proposed approach involves iodine exposures many times higher than established safety limits.
Perhaps the most valuable takeaway is not that high-dose iodine is the answer, but that the relationship between iodine status, adipose tissue physiology, and lipedema deserves more rigorous research.
Women with lipedema deserve treatments grounded in evidence, open-minded scientific inquiry, and a medical community willing to investigate unanswered questions.
References and Further Reading
- Interview with Dr. Jorge Flechas: The Role of Iodine in Reproductive Health
- American Thyroid Association: Potential Risks of Excess Iodine
- Risks of Iodine Excess, Endocrine Reviews (2024)
- Iodine-Induced Thyroid Dysfunction, scientific review
- David Brownstein, MD. Iodine: Why You Need It, Why You Can’t Live Without It.
- Description of the Abraham/Flechas/Brownstein Iodine Protocol
Disclaimer: This article is for educational purposes only and does not constitute medical advice. High-dose iodine supplementation can cause clinically significant thyroid dysfunction and other adverse effects. Anyone considering iodine supplementation, particularly above established nutritional upper limits, should consult a qualified healthcare professional.


